
 Shop Vielight tech















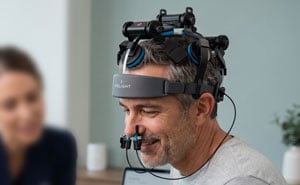


TBI Clinical Results: Vielight itPBM Boosts Neuromuscular Health
A summary of a 2024 open-label pilot study from the University of Utah, in which 43 adults with a history of repeated head impacts investigated intranasal-transcranial PBM at home for eight weeks and completed tests of reaction time, grip strength, dexterity and balance.
Reference: Johnson PK, Fino PC, Wilde EA, et al. The Effect of Intranasal Plus Transcranial Photobiomodulation on Neuromuscular Control in Individuals with Repetitive Head Acceleration Events. Photobiomodulation, Photomedicine, and Laser Surgery. 2024;42(6):404-413. DOI: 10.1089/pho.2023.0178. PMID: 38848287. PMCID: PMC11587703.
About the study
Researchers at the University of Utah School of Medicine and the George E. Wahlen VA Medical Center in Salt Lake City studied adults who reported a history of repeated head impacts, which the authors call repetitive head acceleration events. Earlier research has linked repeated head impacts with changes in balance, reaction time and motor control.
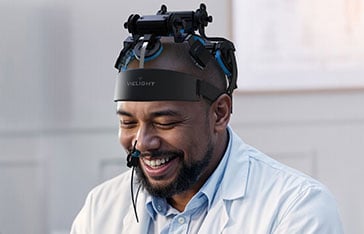
Each participant used a Vielight Neuro Gamma at home for eight weeks. The researchers measured reaction time, grip strength, hand dexterity and balance before and after that period. These tests were part of a larger study that also included cognitive and psychological assessments and brain MRI.
The study was a nonrandomized, single-arm proof-of-concept study: every participant used an active device, and there was no placebo or sham group.
Study details
| Participants | 49 enrolled and 43 completed (39 men, 4 women), aged 18 to 69 (mean 49.5). All reported a history of repeated head impacts or concussion, most from recreational, high school, collegiate or professional sports, and at least one ongoing complaint such as poor sleep, memory difficulty or mood changes. |
| Device | Vielight Neuro Gamma (v3, 2020 model) |
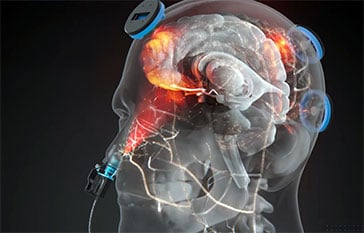
| Light | 810 nm near-infrared LEDs pulsed at 40 Hz (50% duty cycle): four on the scalp, positioned over the medial prefrontal cortex, the left and right angular gyrus areas and the precuneus, plus one intranasal LED. Three scalp LEDs at 100 mW/cm², one at 75 mW/cm², and the intranasal LED at 25 mW/cm². |
| Schedule | 20 minutes every other day for 8 weeks. Some participants could not return for testing until week 10 to 12 and kept using the device until then. |
| Measures | Clinical reaction time (catching a falling stick), Grooved Pegboard Test (hand dexterity), grip strength (Jamar Plus dynamometer), and the Mini Balance Evaluation Systems Test (MiniBEST, scored out of 28) |
Results
Changes were tested with statistical models that accounted for age, and p-values were corrected for multiple comparisons. Effect sizes are Hedges’ g, where the authors treat 0.2 as small, 0.5 as moderate and 0.8 as large.
| Test | Before | After | Change | p-value | Effect size |
|---|---|---|---|---|---|
| Reaction time (ms, lower is faster) | 223.0 | 203.6 | 19.39 ms faster | <0.001 | g = 0.75 |
| Grip strength, dominant hand (kg) | 46.9 | 49.6 | +2.70 kg | 0.003 | g = 0.22 |
| Grip strength, non-dominant hand (kg) | 44.0 | 48.1 | +3.73 kg | <0.001 | g = 0.34 |
| MiniBEST total balance score (out of 28) | 24.7 | 26.1 | +1.32 points | <0.001 | g = 0.51 |
| MiniBEST reactive postural control (recovering from a push or loss of balance) | 4.65 | 5.47 | +0.81 points | <0.001 | g = 0.63 |
| Grooved Pegboard, dominant hand (seconds, lower is faster) | 77.5 | 75.4 | 2.02 s faster | 0.215 (not significant) | Not reported |
| Grooved Pegboard, non-dominant hand (seconds, lower is faster) | 83.6 | 80.3 | 3.27 s faster | 0.068 (not significant) | Not reported |
The other three MiniBEST domains (anticipatory postural adjustments, sensory orientation and dynamic gait) did not change significantly. Reaction time, grip strength and overall balance changes were not influenced by age.
The authors note that some changes fall near or below the size usually considered meaningful. A 1.3-point MiniBEST gain is smaller than the 3.5-point change regarded as detectable in similar populations, although 23% of participants improved by 3 points or more. The grip strength gains were below published estimates of a meaningful change, which range from 5.0 to 6.5 kg.
Adherence
Participants tracked their sessions on a log sheet. Reported adherence to the schedule was 92%, with some short periods of inconsistent use.
The authors’ interpretation
The light was aimed at the head, not at the motor regions of the brain or the muscles, so the authors describe the changes as downstream effects. They suggest several possible explanations, including effects on brain energy metabolism, on brain network connectivity, and on brain wave activity from the 40 Hz pulsing. They also note that another part of the same study reported changes in cognition, mood and sleep, which are known to relate to motor performance.
The authors state that the study was not designed to determine how light applied to the head could affect the neuromuscular system, and that these explanations need to be tested in future work.
Limitations
The authors list these limitations: a small sample, mostly male participants (39 of 43), no control or sham group, a self-reported history of head impacts, self-administered sessions, and usage periods that ranged from 8 to 12 weeks. Participants were asked to keep their normal routines, but changes in exercise or other physical activity were not monitored.
The authors describe the study as a proof of concept and state that larger studies with a control or sham group are needed before the changes can be attributed to the device.
Funding and disclosures
The study was supported in part by the Traumatic Brain Injury and Concussion Center PBM Fund and the Keith Rivera Fund. Vielight provided the devices used in the study. One author, Lawrence Carr, PhD, serves as a consultant for Vielight; the other authors declared no direct conflicts of interest. The study was approved by the Institutional Review Boards of the University of Utah and the VA Salt Lake City Healthcare System.


