
 Shop Vielight tech












The Vielight Vagus: Scientific Foundations
Regulatory note. The Vielight Vagus is a general wellness device. It is not intended to diagnose, treat, cure, or prevent any disease or medical condition. The research summarised below is presented for scientific context. It describes findings from electrical vagus nerve stimulation studies and from photobiomodulation literature. It does not describe validated outcomes for this device.
This One Runs at 100 Hz.
The reason has nothing to do with brain waves, and everything to do with two studies that put stimulation frequencies side by side and measured what actually happened.
The assumption worth checking
If you have looked at non-invasive vagus nerve stimulation before, you have probably seen the same numbers repeated: 10 Hz, 20 Hz, 25 Hz. Low and slow. The reasoning sounds intuitive. The vagus nerve governs rest and recovery, so a gentle rhythm should suit it better than a fast one.
That assumption held mostly because nobody had compared frequencies directly under controlled conditions. When two research groups finally did, the result went the other way.
What the head-to-head comparisons found
At the Martinos Center at Massachusetts General Hospital, Sclocco and colleagues used functional MRI to watch the brainstem respond to auricular vagus nerve stimulation delivered at four frequencies: 2, 10, 25, and 100 Hz. They were looking at the nucleus tractus solitarii, the first relay point for incoming vagal signals. The strongest brainstem response came from the 100 Hz condition, localised to the ipsilateral medulla (Sclocco et al., 2020).
Two years later, an independent group in Japan ran a different test on a different outcome. Yokota and colleagues stimulated 35 healthy adults across a range of frequencies and intensities, and tracked heart rate and heart rate variability. Every frequency reduced heart rate. The effect was most pronounced at 100 Hz, and it required a current of 3.0 mA to appear reliably (Yokota et al., 2022).
Two labs, two continents, two different measurement approaches. One imaged the brainstem directly, the other measured cardiac output at the periphery. Both converged on the same number.
This is why the Vielight Vagus pulses at 100 Hz. Not because 100 Hz sits near the gamma band, and not because of any argument borrowed from cortical oscillation research. Peripheral nerve pulse rate and cortical rhythm are separate phenomena. The rationale here is narrower and better supported: when frequency was tested as a variable, 100 Hz produced the largest response.
Why this nerve gets so much attention
The vagus nerve is the main conduit of the parasympathetic nervous system, and roughly 80 percent of its fibres are afferent, meaning they carry information from the body up to the brain rather than the other way around. It participates in autonomic regulation, and it forms the efferent arm of what Kevin Tracey named the inflammatory reflex, a circuit through which neural activity modulates cytokine release (Tracey, 2002).
Heart rate variability is the most accessible window onto vagal activity. Higher variability generally reflects greater parasympathetic influence on the heart, and it has been studied extensively as a marker of autonomic flexibility (Shaffer and Ginsberg, 2017). A systematic review of transcutaneous vagus nerve stimulation and heart rate variability found effects across multiple studies, though with considerable heterogeneity in protocols and outcomes (Bretherton et al., 2022).
Light and electricity are not doing the same thing
Electrical stimulation works by depolarisation. Current crosses the membrane, the membrane potential shifts past threshold, an action potential fires. It is direct, fast, and well characterised.
Photobiomodulation does not do that. Near-infrared photons are absorbed by chromophores, principally cytochrome c oxidase in the mitochondrial respiratory chain, which alters electron transport and downstream ATP and nitric oxide availability (Karu, 1999; Hamblin, 2016). A separate body of work describes photobiomodulation acting on ion channels, including light-sensitive transient receptor potential channels, which offers a route to altered neuronal excitability that does not depend on injected current (Zhang et al., 2024).
The practical consequence is that the two methods are not interchangeable, and evidence from one does not transfer cleanly to the other. Electrical stimulation studies tell us which frequencies and which anatomical targets are worth investigating. They do not tell us what a light-based device will do.
The open questions we are not going to skip past
We have argued elsewhere that photobiomodulation devices should be judged on delivered dose rather than marketing language. That standard applies to our own products, so here are the three limitations a careful reader should weigh.
Depth.
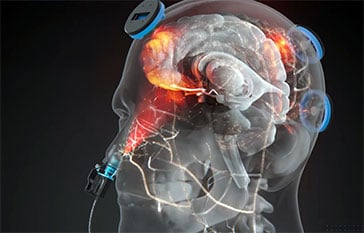
The cervical vagus trunk runs inside the carotid sheath, deep to the sternocleidomastoid. Cadaveric morphometry across 27 specimens put the average anterior-posterior distance from the skin surface at 36.2 mm, with 90 percent of specimens at 41 mm or less (Hammer et al., 2018). Near-infrared light at 810 nm attenuates steeply through skin, subcutaneous fat, platysma, and muscle. We are not claiming that photons arrive at the nerve trunk at that depth in therapeutically meaningful numbers. Any company making that claim, ours included, should be asked to produce transmittance measurements rather than assertions.
Mechanism.
Because of the depth question, direct photonic activation of the vagus trunk is not the most parsimonious explanation for any autonomic change observed with a neck-mounted light device. More plausible candidates include effects on superficial cutaneous afferents in the cervical region, effects on blood transiting the superficial vasculature of the neck, and local anti-inflammatory tissue effects that influence autonomic tone indirectly. These are hypotheses. Distinguishing between them requires experiments that have not yet been run.
Evidence base.
The frequency findings described above come from electrical auricular stimulation, not photonic cervical stimulation. The anatomical target differs, the energy modality differs, and the participants were healthy adults in acute single-session designs. Controlled studies of the Vielight Vagus itself are in planning. Until those are complete and published, the honest description of this device is that it is built on a defensible rationale, not that it has demonstrated outcomes.
Device specifications
| Wavelength | 810 nm near-infrared |
| Pulse frequency | 100 Hz |
| Irradiance at aperture | 50 mW/cm² |
| Placement | Bilateral, over the anterolateral neck at the sternocleidomastoid |
| Form factor | Hands-free headset for repeatable positioning |
| Classification | General wellness device, low risk |
Full specifications and ordering information are on the Vielight Vagus product page. Related patents are listed on our patents page.
Two ways to approach a nerve
|
DRIVE IT Electrical stimulation forces depolarisation. The signal is imposed on the nerve from outside. Well validated, well characterised, and dependent on current reaching the fibre. |
SUPPORT IT Photobiomodulation changes the metabolic and ionic conditions in the tissue it reaches. Nothing is forced. The evidence is earlier stage, and the mechanism in this application remains open. |
Common questions
Why 100 Hz rather than the more common 10 or 25 Hz?
Two independent studies that compared stimulation frequencies directly found the largest response at 100 Hz. Sclocco et al. (2020) measured brainstem activation with fMRI. Yokota et al. (2022) measured heart rate and heart rate variability. Both tested 100 Hz against lower frequencies and found it strongest.
Does the light actually reach the vagus nerve?
The cervical vagus trunk sits roughly 36 mm below the skin on average (Hammer et al., 2018), which is deeper than 810 nm light penetrates with useful irradiance. We do not claim direct photonic activation of the nerve trunk. Any autonomic effect is more likely to involve superficial tissue, cutaneous afferents, or circulating blood. This is an open research question rather than a settled one.
Is this the same as an implanted VNS device?
No. Implanted vagus nerve stimulators are surgically placed prescription medical devices approved for specific conditions such as drug-resistant epilepsy. The Vielight Vagus is a non-invasive general wellness device with no medical indications.
Has the Vielight Vagus been tested in a clinical trial?
Controlled studies are in planning. The evidence discussed on this page comes from the broader vagus nerve stimulation and photobiomodulation literature, not from trials of this device.
References
Bretherton, B., Atkinson, L., Murray, A., Clancy, J., Deuchars, S. A., & Deuchars, J. (2022). Effects of transcutaneous vagus nerve stimulation on heart rate variability: A systematic review. Frontiers in Neuroscience, 16, 913159.
Hamblin, M. R. (2016). Mechanisms and applications of the anti-inflammatory effects of photobiomodulation. AIMS Biophysics, 3(3), 337–361.
Hammer, N., Löffler, S., Cakmak, Y. O., Ondruschka, B., Planitzer, U., Schultz, M., Winkler, D., & Weise, D. (2018). Cervical vagus nerve morphometry and vascularity in the context of nerve stimulation: A cadaveric study. Scientific Reports, 8, 7997.
Karu, T. (1999). Primary and secondary mechanisms of action of visible to near-IR radiation on cells. Journal of Photochemistry and Photobiology B: Biology, 49(1), 1–17.
Sclocco, R., Garcia, R. G., Kettner, N. W., Fisher, H. P., Isenburg, K., Makarovsky, M., Stowell, J. A., Goldstein, J., Barbieri, R., & Napadow, V. (2020). Stimulus frequency modulates brainstem response to respiratory-gated transcutaneous auricular vagus nerve stimulation. Brain Stimulation, 13(4), 970–978.
Shaffer, F., & Ginsberg, J. P. (2017). An overview of heart rate variability metrics and norms. Frontiers in Public Health, 5, 258.
Tracey, K. J. (2002). The inflammatory reflex. Nature, 420(6917), 853–859.
Yokota, H., Edama, M., Hirabayashi, R., Sekine, C., Otsuru, N., Saito, K., Kojima, S., Miyaguchi, S., & Onishi, H. (2022). Effects of stimulus frequency, intensity, and sex on the autonomic response to transcutaneous vagus nerve stimulation. Brain Sciences, 12(8), 1038.
Zhang, Z., Zhang, Z., Liu, P., Xue, X., Zhang, C., Peng, L., Shen, Y., Yang, S., & Wang, F. (2024). The role of photobiomodulation to modulate ion channels in the nervous system: A systematic review. Cellular and Molecular Neurobiology, 44(1), 79.
Vielight devices are general wellness products. They are not intended to diagnose, treat, cure, or prevent any disease or medical condition, including traumatic brain injury, concussion, or chronic traumatic encephalopathy. Consult a qualified healthcare professional regarding any health concern.