
 Shop Vielight tech











Photobiomodulation · Dosimetry · Device physics
The Irradiance Problem: why most brain-PBM helmets never reach the brain
Independent spectroradiometry and a 2025 cadaver study converge on an uncomfortable conclusion: a large class of transcranial-only helmets emit far too little surface power to cross any threshold the human dose-response literature has ever demonstrated.
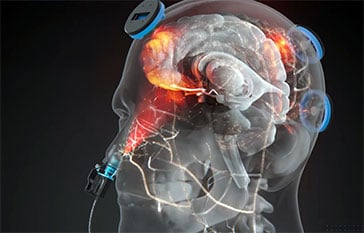
Estimated cortical irradiance windows. The two effects sit at different intensities — vascular/CSF modulation is reachable at low cortical power; direct mitochondrial activation is not. For scale: WALT’s minimum recommended irradiance for treating tissue directly, skin-to-light with no bone involved, is 10 mW/cm². A transcranial helmet that emits less than that at the scalp fails the easy case before it even confronts the hard one — the skull.
01 — The ruleThe Arndt-Schulz curve is a rate law, not a fluence law
Photobiomodulation follows a biphasic dose-response — the Arndt-Schulz law. Too little light does nothing; an intermediate window stimulates; too much inhibits. The detail that consumer marketing routinely gets wrong is that the lower boundary is governed by irradiance (the rate photons arrive, in mW/cm²), not by accumulated fluence (total dose, in J/cm²).
Below the threshold rate, longer sessions accumulate nothing, because the cell dissipates each small perturbation faster than the light delivers it. You cannot compensate for a weak beam by leaving it on longer. This is the single principle that determines whether a device can work at all — and it is the principle that the rest of this analysis tests against real measurements.
So where does the threshold sit? Start with the easiest possible case — light applied straight onto the tissue you want to treat, no bone in the way. For that, the field’s professional body sets a floor. In its 2022 peer-reviewed position paper on cancer-supportive care, the World Association for Photobiomodulation Therapy (WALT) recommends a treatment-surface irradiance of 10–150 mW/cm² for directly-treated tissue such as skin or oral mucosa. That is PBM on the simplest terms it ever operates under: the light source is touching the target, and nothing absorbs or scatters it on the way.
Keep that lower bound in mind, because it frames two separate tests a brain helmet has to pass. The easy test: does it even emit WALT’s 10 mW/cm² minimum at the scalp — the bar for treating tissue you’re touching directly? The hard test, which only matters if it passes the first: does enough of that light survive the skull to do anything at the cortex? A transcranial device that fails the easy test never reaches the hard one.
The professional floor
WALT recommends a treatment-surface irradiance of 10–150 mW/cm² for directly-treated tissue — the simplest case in all of PBM.
WALT 2022 Position Paper. This is a surface-irradiance recommendation for direct tissue targets such as skin and oral mucosa — not a transcranial or cortical-mitochondrial threshold.
02 — The skullWhat a 2025 cadaver study found about transcranial penetration
A 2025 study in Brain Stimulation by Tittelmeier and colleagues measured how much near-infrared light actually crosses the intact human skull — shaved skin, subcutaneous tissue, cranial bone, and dura mater all present — and then tested whether that surviving fraction could activate mitochondria in human neurons and in C. elegans.
The devices they tested were two LED helmets, an 810 nm and a 1070 nm unit, both built on the Suyzeko GY-PDT1 photobiomodulation helmet platform. This matters for what comes next: the 1070 nm helmet measured here is built on the same Suyzeko platform that the consumer Neuronic Neuradiant 1070 is based on, as documented in independent spectroradiometry (Section 03). The device whose skull penetration was measured in this study, in other words, shares its underlying hardware with a 256-LED helmet sold to consumers as a brain-health device. Tittelmeier’s conclusion was blunt: the light reaching brain tissue through this transcranial route was insufficient to stimulate cytochrome c oxidase (COX) activity or to induce the protective mitochondrial stress responses that the therapy’s proposed mechanism depends on. As reported, the 810 nm helmet delivered roughly 0.71% transmittance through the calvaria and the 1070 nm helmet roughly 0.45% — with the longer 1070 nm wavelength penetrating less, not more, despite frequently being marketed on the promise of deeper reach.
“The tested devices do not penetrate the human skull in sufficient quantities to stimulate mitochondrial activity.” — Tittelmeier et al., Brain Stimulation, 2025 (paraphrasing the study’s stated conclusion).

03 — The measurementsIndependent spectroradiometry of three helmets
How much surface power do these helmets actually emit? The PBM Foundation, working with Optronic Labs on a NIST-traceable calibrated spectroradiometer, measured three devices and compared each manufacturer’s declared figure against the calibrated result. The findings matter because the helmet platform Tittelmeier tested for skull penetration is the same one measured here for surface power.
| Device & measured wavelength | Declared | Measured surface irradiance | Verdict |
|---|---|---|---|
| Suyzeko NIR helmetmeasured 811 nm · 256 LEDs | 24 mW/cm² | 4.74 mW/cm² | 81% below its own claim; ~96% weaker than peak sunlight. |
| Neuronic Neuradiant 1070measured 1059 nm · 256 LEDs · same Suyzeko platform | 20–40 mW/cm² | 6.22 mW/cm² | ~79% below claim. An independent 2026 review measured 7–9 mW/cm² and put through-skull irradiance below detection. |
| Vielight Neuromeasured 810 nm · high-power Vie-LEDs | 75–100 mW/cm² | 277.5 mW/cm² | Understated by the maker; the only device measured above the WALT and Baycrest ranges. |
A second, fully independent test reaches the same place — and adds the number the others left out. Psychiatrist Dr. Cody Rall ran his own spectrometer measurements of both devices, recording not only surface output but how much light survives an actual human skull. Because he has no affiliation with either manufacturer, the close agreement with the calibrated PBM Foundation figures is meaningful corroboration rather than a vendor’s own chart.
| Device (measured wavelength) | At the device surface | Through a human skull |
|---|---|---|
| Neuronic Neuradiant 1070measured 1033 nm | 3–5 mW/cm² | 0.35 mW/cm² |
| Vielight Neuro Pro 2measured 807 nm | 250–300 mW/cm² | 15–20 mW/cm² |
Independent spectrometer testing by Dr. Cody Rall (US Navy Psychiatrist, Techforpsych). Watch the comparison video here. On his measurements, the Vielight delivered roughly 40 to 60 times more light through the skull than the Neuronic. Note that 0.35 mW/cm² still sits well below the thresholds discussed below — the point is the gap between devices, not that either clears every bar.
Now apply the two tests from Section 01. The easy test first: WALT’s minimum irradiance for treating tissue you touch directly — no bone, no scatter — is 10 mW/cm². These helmets emit roughly 5–6 mW/cm² at the scalp. They fall below the field’s floor for the simplest form of PBM there is, the kind where the light is pressed straight against the target. And that is the generous reading, because a brain helmet is not treating the scalp — it is trying to treat the cortex underneath it. The hard test, surviving the skull, never comes into play: the device has already failed the easy one.
This is a measurement of emitted surface power, not of cortical delivery — the report is careful about that distinction, and so are we. But it establishes the input to every penetration calculation: if only single-digit mW/cm² leaves the device, the fraction surviving the skull is smaller still.
04 — The gapPutting the surface power against a human dose-response curve
What surface irradiance does it actually take to move the needle in a living human brain? The most direct answer comes from a 2025 fMRI trial run at Baycrest using Vielight-supplied research lasers, which measured real-time cerebrospinal fluid (CSF) dynamics in 45 healthy adults across a range of irradiances.
For transcranial forehead delivery, the trial tested surface irradiances of 100, 150, and 200 mW/cm². It found a measurable CSF response across that range, with the peak response at 150 mW/cm² for 808 nm light in specific regions — a clean in-vivo demonstration of the biphasic curve, since the highest dose was not the most effective. The trial did not test anything below 100 mW/cm² transcranially, so it makes no claim about a precise cut-off. But the implication for low-power hardware is direct:
Measured surface irradiance, common 256-LED dome helmets: ~5–6 mW/cm²
——————————————————————
The dome helmets emit roughly 1/20th of the weakest dose any controlled human trial has shown to produce a brain response.
Stack the two findings and the conclusion is hard to avoid. Tittelmeier shows the surviving cortical fraction from these helmets is too small to activate mitochondria. The independent spectroradiometry shows they emit only single-digit mW/cm² to begin with. And the human dose-response data shows transcranial PBM needed an order of magnitude more surface power than that just to register a vascular effect. A device emitting 5–6 mW/cm² at the scalp is operating below the floor of every effect anyone has demonstrated.
When a device cannot cross the threshold its proposed mechanism requires, yet users still report benefits, the honest explanation lies elsewhere: expectancy and placebo, the relaxation of sitting still under a warm glow, and the well-documented strength of placebo in subjective neuropsychiatric outcomes. These effects are real and can matter to people — but they are not photobiomodulation as the science defines it. Tellingly, the Baycrest team built placebo controls into their trial (participants could not see the light and felt no heat) precisely so that the CSF response they measured could not be attributed to expectancy. A device that produces only the expectancy is the mirror image of that design.
05 — The shortcutWhy intranasal delivery reaches deep structures the skull blocks
If the calvaria is the problem, the most effective response is not simply to push more power against it — it is to go around it. This is the logic of intranasal photobiomodulation (iPBM), and the same Baycrest trial put it to a direct test.
Transcranial only (tPBM)Light must survive scalp, hair, and the full thickness of the skull before any reaches the cortex. At single-digit surface power, almost nothing does. |
Intranasal + transcranial (itPBM)The nasal channel routes light through the thin, porous cribriform plate — straight toward deep, central structures — at a fraction of the energy. |
The roof of the nasal cavity is the cribriform plate of the ethmoid bone — a thin, porous structure whose thickness is a small fraction of the frontal skull’s. It sits directly beneath the olfactory bulbs and the ventral frontal cortex, and it lies on the natural olfactory pathway by which CSF drains from the brain. Light delivered through the nostril bypasses hair, scalp, the thick outer skull tables, and the diploic space entirely, taking a short, low-attenuation route to ventral and subcortical structures that transcranial light struggles to reach at all.
The trial’s result was striking. Intranasal delivery at just 5, 7, and 9 mW/cm² produced CSF responses comparable to forehead delivery at 100–200 mW/cm² — depositing only 3–5% of the energy for an equivalent effect. The authors called this “unexpected and contrary to our hypothesis” that the response would scale with raw irradiance, and attributed it to the nasal route’s proximity to the olfactory CSF conduit.
There is a second advantage, and it is one of equity as much as efficiency. Transcranial forehead delivery is attenuated by skin melanin: the Baycrest data showed that fairer skin (higher Individual Typology Angle) was associated with significantly stronger CSF responses, because epidermal melanin absorbs near-infrared photons before they reach the skull. The same fixed surface dose therefore delivers a different therapy to different patients. The intranasal route bypasses the epidermis, and the authors note the melanin dependence does not apply to it. Light through the nose reaches the brain on terms that do not depend on the color of the skin it would otherwise have to cross.
The intranasal advantage
Intranasal PBM produced a comparable CSF response to forehead PBM while depositing only 3–5% of the energy — and without the skin-tone dependence transcranial delivery carries.
Summary of Baycrest fMRI findings, Brain Stimulation, 2025.
06 — The takeawayWhat this means for choosing a device
1 · Independently measured irradiance?Not the declared figure. Independent testing found two popular dome helmets emitting ~80% below their own specs, in the single-digit mW/cm² range. |
2 · Does it clear a real threshold?WALT’s minimum for treating tissue directly is 10 mW/cm²; the only human transcranial dose-response data starts at 100 mW/cm². Single-digit power clears neither. |
3 · Wavelength vs mechanism810 nm is absorbed at cytochrome c oxidase and penetrates the skull more than 1070 nm. A longer wavelength is not automatically a deeper one. |
4 · LED count is not dose256 weak diodes produce a low surface irradiance regardless of how many there are. Coverage is not intensity. |
5 · Fight the skull, or bypass it?The intranasal cribriform route reached equivalent CSF effects at 3–5% of the transcranial energy, and removed skin tone as a variable. |
The bottom lineSpectroradiometry says what leaves the device; a cadaver study says how little survives the skull; an fMRI trial says how much you needed. The three draw one clear line. |
The physics here is no longer speculative. Independent spectroradiometry tells you what leaves the device; a cadaver penetration study tells you how little survives the skull; and a human fMRI dose-response trial tells you how much you needed in the first place. Read together, they draw a clear line between hardware that can engage the mechanism and hardware that, whatever it is doing for its users, is not delivering meaningful light to the brain.
References
- Tittelmeier et al. (2025). Insufficient low-level near-infrared light penetration challenges the efficacy of transcranial photobiomodulation. Brain Stimulation. View article
- PBM Foundation & Optronic Labs (2024). Multiple Device Case Study: Vielight Neuro, Neuronic Neuradiant, Joovv. Calibrated surface-irradiance measurement (unpublished case study). View report
- Baycrest (2025). Real-time fMRI study of transcranial and intranasal PBM effects on cerebrospinal fluid dynamics in 45 healthy adults. Brain Stimulation. View article
- WALT Position Paper (2022). Photobiomodulation therapy in management of cancer therapy-induced side effects: recommended treatment-surface irradiance of 10–150 mW/cm². World Association for Photobiomodulation Therapy. View paper (PMC)
Notes on sourcing. The PBM Foundation case study is an independent (non-peer-reviewed) measurement exercise conducted with Optronic Labs; figures cited are as reported in that document. The 0.71% / 0.45% transmittance figures are as reported from Tittelmeier et al.; the study’s primary stated conclusion is that the tested transcranial helmets delivered insufficient cortical light to activate mitochondria. The WALT 10–150 mW/cm² figure is a treatment-surface irradiance recommendation for directly treated tissue (from WALT’s 2022 cancer-supportive-care position paper) and is cited here as the field’s general standard for effective surface irradiance, not as a brain-specific or cortical-mitochondrial threshold. The Baycrest trial measured CSF dynamics as a surrogate for glymphatic flow in healthy young adults and does not by itself establish clinical outcomes. This article discusses device physics and published research; it is not medical advice.