
 Shop Vielight tech












Enhancing the Default Mode Network (DMN)
Vielight devices are general wellness products. They are not intended to diagnose, treat, cure, or prevent any disease or medical condition, including traumatic brain injury, concussion, or chronic traumatic encephalopathy. The research summarized below is presented for educational purposes and does not constitute claims about device performance or indications for use.
Enhancing the Default Mode Network: why a headset only reaches half of it
The most-targeted network in brain photobiomodulation runs deeper than the skull. Here is what that means for how light is delivered.
There is a reasonable assumption built into most brain photobiomodulation devices on the market: that the brain is a surface you can illuminate. Place near-infrared emitters against the scalp, and the cortex underneath receives energy. Add more emitters, add more coverage.
That assumption works for the cortex. It does not work for the Default Mode Network.
The DMN is the network that nearly every brain PBM device claims to target, and for good reason. It is the network most closely tied to memory, self-reference, imagination and social cognition. But it is not a patch of surface tissue. It is a distributed system whose hubs sit at the midline, behind the sinuses, and deep in the medial temporal lobes. A transcranial array reaches the outer nodes of that network and stops.
This is the reason the Vielight Neuro was engineered as an intranasal-transcranial system rather than a headset alone.
What the imaging is starting to show
Until recently this was an engineering argument rather than an observed one. That is changing.
Researchers at the Rotman Research Institute at Baycrest and the University of Toronto used BOLD-fMRI to compare where the brain responds when near-infrared light is delivered to the forehead versus through the nasal cavity. Their reported finding is that intranasal delivery produced responses in subcortical tissue, including the thalamus, which forehead-only delivery did not reach. The authors describe intranasal delivery as an energy-efficient route to cortical and subcortical stimulation. [44]
A companion study from the same group, published in Brain Stimulation, reported that four minutes of pulsed intranasal PBM was associated with measurable changes in cerebrospinal fluid dynamics, at roughly five percent of the energy required by transcranial delivery to produce a comparable effect. [45]
Note on evidence status: reference [44] is a preprint and has not yet completed peer review. Reference [45] is peer reviewed. Both were conducted in healthy adults and describe physiological responses, not clinical outcomes.
Taken together, these observations point at something specific. The route matters, not just the dose. Two devices delivering the same wavelength at the same frequency can produce different spatial coverage depending on where the light enters.
What the Default Mode Network actually is
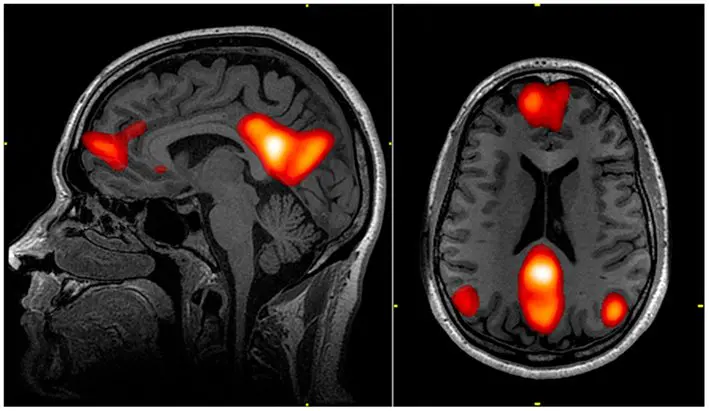
The DMN is a set of highly interconnected brain regions responsible for internal modes of cognition. Diffusion MRI and resting-state fMRI show that neurons across these regions are joined by large axonal tracts, which is why their activity is correlated with one another. [22][23]
The word “default” is a historical accident. The network was named for its heightened activity during idle periods, which implied it was simply what the brain does when nothing else is happening. Later work showed this to be a misnomer. The DMN is also highly active during directed internal thought: recalling your past, imagining your future, considering what someone else is thinking. [41][42][43]
The picture has widened again since. The DMN is now known to engage during tasks driven by external perceptual input, including language comprehension and social perception. Work published in PNAS in 2026 proposed an organizational principle to explain how one network handles both, describing sender and receiver subdivisions within the DMN that separate perceptually driven from memory-guided processing. [47]
Its hubs include the medial prefrontal cortex (mPFC), the ventromedial prefrontal cortex (vmPFC), the precuneus, the inferior parietal lobule (IPL), the lateral temporal cortex (LTC), and the posterior cingulate cortex (pCC). The hippocampal formation, within the medial temporal lobes, is closely coupled to the network.
Its documented roles cluster into three groups. [22][23]
| The neurological basis of self | Autobiographical memory, self-reference, and reflection on one’s own emotional state. |
| Thinking about others | Theory of mind, empathy and reading the emotions of others, and moral reasoning. |
| Moving through time | Recalling the past, imagining the future, episodic memory, and story comprehension. |
Is the DMN the seat of consciousness?
This claim circulates, and it is worth addressing directly, because the accurate answer is more interesting than the claim.
No, and consciousness research does not frame it that way. The two dominant theories point elsewhere. Global Neuronal Workspace Theory locates conscious experience in the global broadcasting of information across prefrontal and parietal regions. Integrated Information Theory locates it in a posterior temporo-parietal-occipital “hot zone.” In 2025, the Cogitate Consortium published an adversarial collaboration in Nature that tested both theories directly across 256 participants using fMRI, MEG and intracranial EEG. Information about conscious content was found in visual, ventrotemporal and inferior frontal cortex. The results challenged key tenets of both theories, and the DMN was not the proposed answer in either. [48]
What the DMN evidence does show
DMN connectivity breaks down under anesthesia and in disorders of consciousness, and tends to reorganize as consciousness returns. That is a real and repeatedly observed relationship. It establishes the DMN as a correlate of conscious state, and a plausible imaging biomarker for tracking recovery. It does not establish it as the source.
A 2026 study in Brain examining surgically disconnected hemispheres made the distinction explicit. The authors reported that the presence of DMN activity fulfils a necessary condition for preserved consciousness, then stated plainly that this does not support the reverse inference that such activity alone confirms consciousness is present. [49]
The evidence that cuts the other way
Reviews of DMN topography across altered states describe something that a simple “seat of consciousness” account cannot absorb. Both reduced states, such as anesthesia and unresponsive wakefulness syndrome, and elevated states, such as meditation and psychedelic experience, are characterized by a flattening of the brain’s DMN-centric organization. They differ in their dynamics, not in the direction of that flattening. [50]
If the DMN were the seat of consciousness, suppressing its dominance should suppress experience. In psychedelic states it does close to the opposite.
Where the idea comes from
A 2025 review by Luppi, Lyu and Stamatakis proposed an integrative view of the DMN as the anatomical and functional nexus for convergence and divergence in the human brain, arguing that a breakdown of DMN spatiotemporal continuity collapses the cortical functional hierarchy and the integration of self and world into a coherent stream. [51] It is a serious proposal, and it is a hypothesis, presented as one by its authors rather than as a settled finding.
There is one substantive overlap worth noting. The precuneus and posterior cingulate cortex sit within both the DMN and the posterior hot zone that Integrated Information Theory identifies. So these hubs are of genuine interest to consciousness researchers, whatever the eventual verdict on the network as a whole.
The better-supported claim, and the one this article rests on, is narrower and more useful: the DMN appears to underpin the narrative self, the sense of a continuous person with a past, a future and a social world. That is not the same as consciousness, and it is interesting enough on its own terms.
The hubs, and how each one is reached
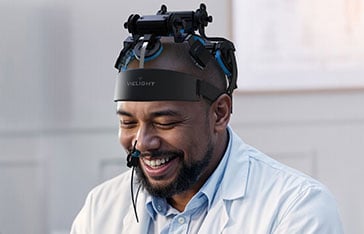
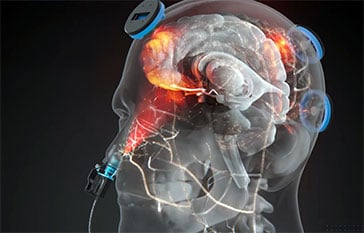
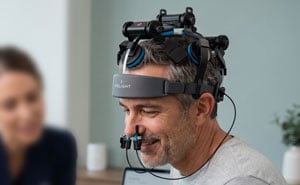
The Vielight Neuro places four transcranial LEDs over the outer nodes of the network and one intranasal emitter that delivers light through the nasal cavity toward the deeper anterior and medial structures. The demonstration below shows the resulting energy footprint across a calvaria model.
Reached transcranially
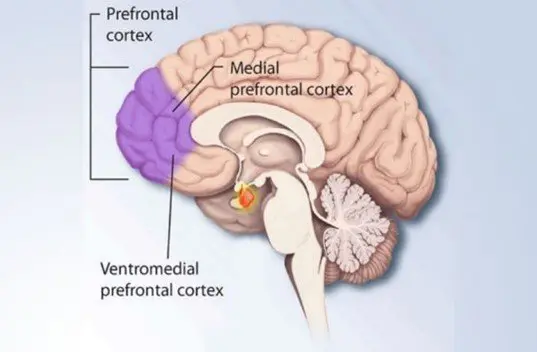
Medial prefrontal cortex (mPFC)
Behind the forehead, within the frontal lobe. The mPFC plays a regulatory role in attention, inhibitory control, habit formation, and working, spatial and long-term memory. [1] It is also one of the more commonly affected regions in head injury.
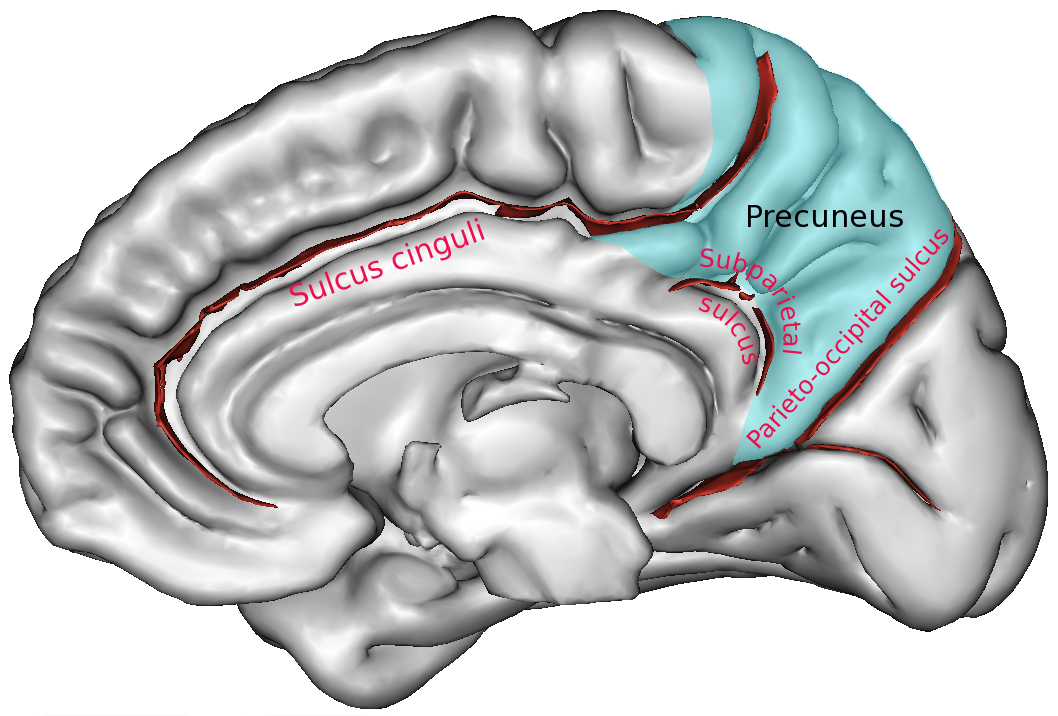
Precuneus
A section of the superior parietal lobe, and widely considered the core hub of the DMN. [9] Its cognitive roles include self-consciousness [5], spatial memory [6], episodic memory [7] and source memory, meaning recall of where a memory or piece of knowledge came from. [8] It also supports motor imagery [10], the mental rehearsal of action used in sport training and neurological rehabilitation, and motor coordination. [11]
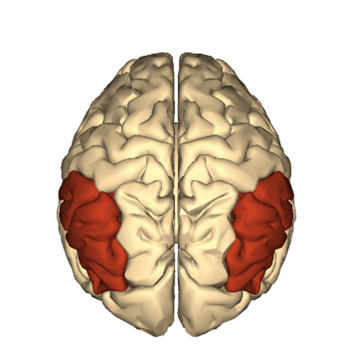
Inferior parietal lobule (IPL)
Located bilaterally in the rear half of the brain. The IPL is a convergence zone for several of the most distinctive human capacities: language, pattern learning, mathematical operations [12], and the perception of emotion in faces.
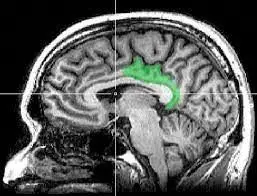
Posterior cingulate cortex (pCC)
Found around the midline. The pCC is a central node of the DMN, highly connected, and communicating with several brain networks at once. [13] Cerebral blood flow and metabolic rate in the pCC run roughly 40 percent above the brain-wide average. [14][15]
It has been linked to spatial memory, autobiographical memory [16], and working memory performance. [17] It is also implicated in the dorsal attention network and the frontoparietal control network. [14] Notably, the pCC activates during self-related thinking and deactivates during meditation and effortless mind wandering. [20]
Temporal lobes
Sitting behind the ears, the temporal lobes are the second largest lobe and process visual stimuli such as faces and scenes, auditory signals including speech, language comprehension, and visual memory. The dominant lobe, usually the left, handles language and verbal recall. The non-dominant lobe handles non-verbal material such as visuospatial information and music.
Where the intranasal route matters
Ventromedial prefrontal cortex (vmPFC)
The vmPFC sits directly above the eyes and nose, at the base of the frontal lobe. It contributes to decision-making, self-control, and the regulation of emotional responses [2][3], as well as the cognitive evaluation of morality. [4]
Its position is the problem. Reaching the vmPFC from the scalp means traversing the full thickness of the frontal bone and the tissue above it. The nasal cavity sits immediately beneath it, separated by comparatively thin bone. This is the anatomical basis for Vielight’s patented intranasal approach.
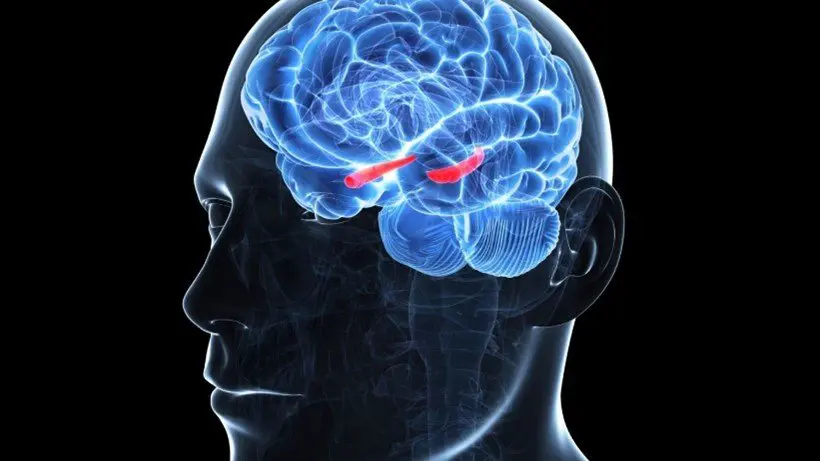
Hippocampal area and medial temporal structures
The hippocampus lies within the temporal lobes and supports the conversion of short-term to long-term memory, along with the spatial memory that enables navigation. It is among the first regions to show damage in Alzheimer’s disease and other dementias, which is why short-term memory loss and disorientation appear early. [18]
Although it is a small subregion, it is deep, and depth is precisely what transcranial delivery struggles with.
Why researchers keep returning to the DMN
Altered DMN connectivity has been observed in a range of neurological and neuropsychiatric conditions, including Alzheimer’s disease, Parkinson’s disease, autism, schizophrenia, depression, multiple sclerosis and post-traumatic stress disorder. [25][26][27][28][29] That pattern is what has made the network a recurring focus of investigator-led research.
The table below summarizes findings reported by independent research groups that used Vielight devices, alongside what the literature says about DMN involvement in each condition. These are published research observations. They are not indications for use, and they do not describe intended uses of Vielight general wellness products.
| Condition | Reported DMN involvement | Published research using Vielight devices |
|---|---|---|
| Alzheimer’s disease | Reduced functional connectivity between posterior and anterior portions of the DMN. [31] Overlap between DMN topography and patterns of amyloid deposition. [32] | Chao (2019) reported increased connectivity between the posterior cingulate cortex and lateral parietal nodes of the DMN in the PBM group of a pilot trial. [36] Saltmarche et al. (2017), a case series using transcranial plus intranasal PBM, reported improvement on MMSE and ADAS-cog over 12 weeks, with no negative side effects noted. [37] |
| Parkinson’s disease | Coordinated activity between the striatum and the DMN. [33] Disruption across the DMN and central executive network. [34] | Liebert et al. (2021), a proof-of-concept study at the University of Sydney, reported improvements in mobility, cognition, dynamic balance and fine motor skill over 12 weeks. [38] The protocol combined the Vielight Neuro Gamma and intranasal Gamma with neck and abdominal PBM delivered by a separate, non-Vielight device, so the effects cannot be attributed to Vielight devices alone. |
| Head impact and TBI | DMN connectivity strength has been reported to predict emotion recognition and social integration following TBI. [30] | Chao et al. (2020) reported increased perfusion in frontal, temporal and occipital regions and the hippocampus in a concussion case study. [39] Lindsey et al. (2026), a randomized, double-blind, sham-controlled trial of 26 NCAA Division I football players published in the Journal of Neurotrauma, used diffusion MRI to examine white-matter microstructure across a 16-week season with the Neuro Gamma. [46] |
| Autism spectrum disorder | Structural and functional disruption to key DMN nodes and their connectivity has been described as contributing to ASD symptomatology. [35] | Pallanti et al. (2022), a retrospective study of 21 children using the Vielight Neuro Duo over six months, reported reductions in CARS scores, noncompliant behaviour, parental stress and cognitive rigidity, alongside improvements in attention and sleep quality. [40] |
These studies vary in design and size. Several are pilot studies, case series or retrospective analyses without control groups, and their findings require replication in larger controlled trials before conclusions can be drawn.
The engineering rationale
The thesis behind the Vielight Neuro was to select the DMN and its hubs deliberately, because of the roles they play in self-awareness, memory, emotion, imagination, and mathematical and language processing.
Choosing the target was the first decision. Choosing the delivery route was the second, and it is the one that separates itPBM from transcranial-only approaches. Four transcranial emitters cover the outer nodes. The intranasal emitter addresses the anterior and medial structures that a headset cannot reach efficiently, and the Baycrest imaging work suggests that route reaches deeper than the cortex. [44][45]
A network is only as well served as its least-reachable hub. That is the whole argument.
Read more on the Vielight Neuro’s design

General wellness device. Not intended to diagnose, treat, cure, or prevent any disease. Individual results vary. Research cited on this page was conducted by independent investigators and is presented for educational purposes only.
References
- Jobson DD, Hase Y, Clarkson AN, Kalaria RN. The role of the medial prefrontal cortex in cognition, ageing and dementia. Brain Commun. 2021;3(3):fcab125.
- Boes AD, Grafft AH, Joshi C, et al. Behavioral effects of congenital ventromedial prefrontal cortex malformation. BMC Neurology. 2011;11:151.
- Bechara A, Tranel D, Damasio H. Characterization of the decision-making deficit of patients with ventromedial prefrontal cortex lesions. Brain. 2000;123(11):2189-2202.
- Koenigs M, Young L, Adolphs R, et al. Damage to the prefrontal cortex increases utilitarian moral judgements. Nature. 2007;446(7138):908-911.
- Lou HC, Luber B, Crupain M, et al. Parietal cortex and representation of the mental Self. PNAS. 2004;101(17):6827-6832.
- Wallentin M, Roepstorff A, Glover R, Burgess N. Parallel memory systems for talking about location and age in precuneus, caudate and Broca’s region. NeuroImage. 2006;32(4):1850-1864.
- Lundstrom BN, Petersson KM, Andersson J, et al. Isolating the retrieval of imagined pictures during episodic memory. NeuroImage. 2003;20(4):1934-1943.
- Lundstrom BN, Ingvar M, Petersson KM. The role of precuneus and left inferior frontal cortex during source memory episodic retrieval. NeuroImage. 2005;27(4):824-834.
- Cavanna AE. The precuneus and consciousness. CNS Spectrums. 2007;12(7):545-552.
- Cavanna A, Trimble M. The precuneus: a review of its functional anatomy and behavioural correlates. Brain. 2006;129(3):564-583.
- Wenderoth N, Debaere F, Sunaert S, Swinnen SP. The role of anterior cingulate cortex and precuneus in the coordination of motor behaviour. Eur J Neurosci. 2005;22(1):235-246.
- Numssen O, Bzdok D, Hartwigsen G. Functional specialization within the inferior parietal lobes across cognitive domains. eLife. 2021;10:e63591.
- Leech R, Braga R, Sharp DJ. Echoes of the brain within the posterior cingulate cortex. J Neurosci. 2012;32(1):215-222.
- Leech R, Sharp DJ. The role of the posterior cingulate cortex in cognition and disease. Brain. 2013;137(1):12-32.
- Pearson JM, Heilbronner SR, Barack DL, et al. Posterior cingulate cortex: adapting behavior to a changing world. Trends Cogn Sci. 2011;15(4):143-151.
- Maddock RJ, Garrett AS, Buonocore MH. Remembering familiar people: the posterior cingulate cortex and autobiographical memory retrieval. Neuroscience. 2001;104(3):667-676.
- Kozlovskiy SA, Vartanov AV, Nikonova EY, et al. The cingulate cortex and human memory processes. Psychology in Russia. 2012;5:231-243.
- Dubois B, Hampel H, Feldman HH, et al. Preclinical Alzheimer’s disease: definition, natural history, and diagnostic criteria. Alzheimers Dement. 2016;12(3):292-323.
- Smith EE, Kosslyn SM. Cognitive Psychology: Mind and Brain. Prentice Hall; 2007:21,194-199,349.
- Garrison KA, Santoyo JF, Davis JH, et al. Effortless awareness: using real time neurofeedback to investigate correlates of posterior cingulate cortex activity in meditators’ self-report. Front Hum Neurosci. 2013;7:440.
- Meguro K. Neocortical and hippocampal glucose hypometabolism following neurotoxic lesions of the entorhinal and perirhinal cortices in the non-human primate as shown by PET. Brain. 1999;122(8):1519-1531.
- Andrews-Hanna JR. The brain’s default network and its adaptive role in internal mentation. The Neuroscientist. 2012;18(3):251-270.
- Horn A, Ostwald D, Reisert M, Blankenburg F. The structural-functional connectome and the default mode network of the human brain. NeuroImage. 2013;102:142-151.
- Buckner RL, Andrews-Hanna JR, Schacter DL. The brain’s default network: anatomy, function, and relevance to disease. Ann N Y Acad Sci. 2008;1124(1):1-38.
- Van Eimeren T, Monchi O, Ballanger B, Strafella AP. Dysfunction of the default mode network in Parkinson disease. Arch Neurol. 2009;66(7):877-883.
- Tessitore A, Esposito F, Vitale C, et al. Default-mode network connectivity in cognitively unimpaired patients with Parkinson disease. Neurology. 2012;79(23):2226-2232.
- Rocca MA, Valsasina P, Absinta M, et al. Default-mode network dysfunction and cognitive impairment in progressive MS. Neurology. 2010;74(16):1252-1259.
- Daniels JK, Frewen P, McKinnon MC, Lanius RA. Default mode alterations in posttraumatic stress disorder related to early-life trauma. J Psychiatry Neurosci. 2011;36(1):56-59.
- Mohan A, Roberto AJ, Mohan A, et al. The significance of the default mode network (DMN) in neurological and neuropsychiatric disorders: a review. Yale J Biol Med. 2016;89(1):49-57.
- Lancaster K, Venkatesan UM, Lengenfelder J, Genova HM. Default mode network connectivity predicts emotion recognition and social integration after traumatic brain injury. Front Neurol. 2019;10:825.
- Hafkemeijer A, van der Grond J, Rombouts SA. Imaging the default mode network in aging and dementia. Biochim Biophys Acta. 2012;1822(3):431-441.
- Mormino EC, Smiljic A, Hayenga AO, et al. Relationships between beta-amyloid and functional connectivity in different components of the default mode network in aging. Cereb Cortex. 2011;21(10):2399-2407.
- Kwak Y, Peltier S, Bohnen NI, et al. Altered resting state cortico-striatal connectivity in mild to moderate stage Parkinson’s disease. Front Syst Neurosci. 2010;4:143.
- Putcha D, Ross RS, Cronin-Golomb A, et al. Altered intrinsic functional coupling between core neurocognitive networks in Parkinson’s disease. Neuroimage Clin. 2015;7:449-455.
- Padmanabhan A, Lynch CJ, Schaer M, Menon V. The default mode network in autism. Biol Psychiatry Cogn Neurosci Neuroimaging. 2017;2(6):476-486.
- Chao LL. Effects of home photobiomodulation treatments on cognitive and behavioral function, cerebral perfusion, and resting-state functional connectivity in patients with dementia: a pilot trial. Photobiomodul Photomed Laser Surg. 2019;37(3):133-141.
- Saltmarche AE, Naeser MA, Ho KF, Hamblin MR, Lim L. Significant improvement in cognition in mild to moderately severe dementia cases treated with transcranial plus intranasal photobiomodulation: case series report. Photomed Laser Surg. 2017;35(8):432-441.
- Liebert A, Bicknell B, Laakso EL, et al. Improvements in clinical signs of Parkinson’s disease using photobiomodulation: a prospective proof-of-concept study. BMC Neurol. 2021;21(1):256.
- Chao L, Barlow C, Karimpoor M, Lim L. Changes in brain function and structure after self-administered home photobiomodulation treatment in a concussion case. Front Neurol. 2020;11:952.
- Pallanti S, Di Ponzio M, Grassi E, Vannini G, Cauli G. Transcranial photobiomodulation for the treatment of children with autism spectrum disorder (ASD): a retrospective study. Children. 2022;9(5):755.
- Andreasen NC, O’Leary DS, Cizadlo T, et al. Remembering the past: two facets of episodic memory explored with positron emission tomography. Am J Psychiatry. 1995;152:1576-1585.
- Buckner RL, Carroll DC. Self-projection and the brain. Trends Cogn Sci. 2007;11:49-57.
- Spreng RN, Mar RA, Kim AS. The common neural basis of autobiographical memory, prospection, navigation, theory of mind, and the default mode: a quantitative meta-analysis. J Cogn Neurosci. 2009;21:489-510.
- Van Lankveld H, Chen JX, Zhong XZ, Chen JJ. Intranasal photobiomodulation: an energy efficient paradigm for cortical and subcortical stimulation. bioRxiv. 2026;2026.03.03.709361. Preprint, not certified by peer review.
- Motsenyat A, Zhong XZ, Van Lankveld H, Chen JX, Mathew A, Chen JJ. Modulating cerebrospinal fluid dynamics using pulsed photobiomodulation. Brain Stimul. 2026;19(1):102988.
- Lindsey HM, et al.; Wilde EA. Transcranial photobiomodulation promotes neurological resilience in current collegiate American football players exposed to repetitive head acceleration events. J Neurotrauma. 2026.
- Zhang M, et al. Sender-receiver subdivisions of the default mode network in perceptual and memory-guided cognition. PNAS. 2026. doi:10.1073/pnas.2528851123
- Cogitate Consortium; Ferrante O, Gorska-Klimowska U, et al. Adversarial testing of global neuronal workspace and integrated information theories of consciousness. Nature. 2025;642(8066):133-142. doi:10.1038/s41586-025-08888-1
- Default-mode network activity is retained in the isolated hemisphere of people after hemispherotomy. Brain. 2026.
- Buccellato A, Northoff G, et al. The Default Mode Network and inner time consciousness. Curr Opin Behav Sci. 2025. doi:10.1016/j.cobeha.2025.101505
- Luppi AI, Lyu D, Stamatakis EA. Core of consciousness: the default mode network as nexus of convergence and divergence in the human brain. Curr Opin Behav Sci. 2025.


